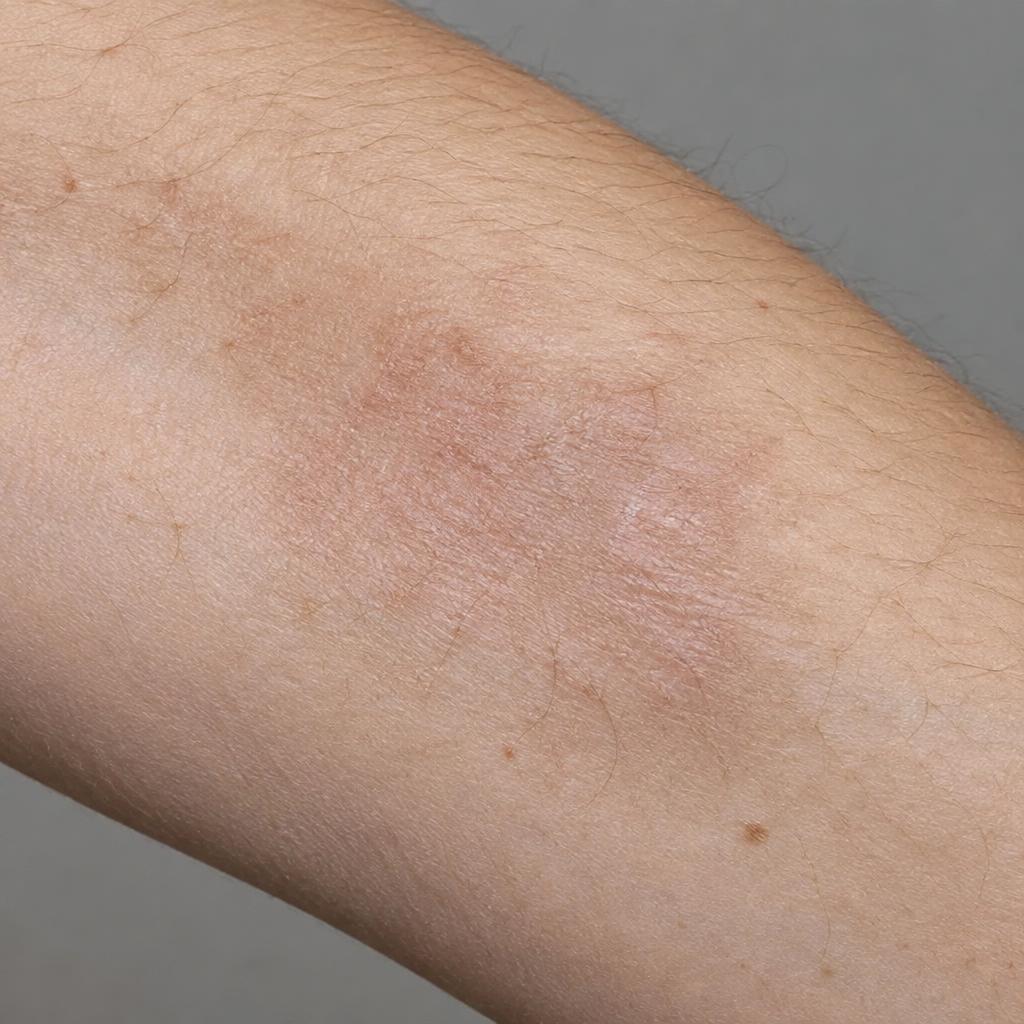
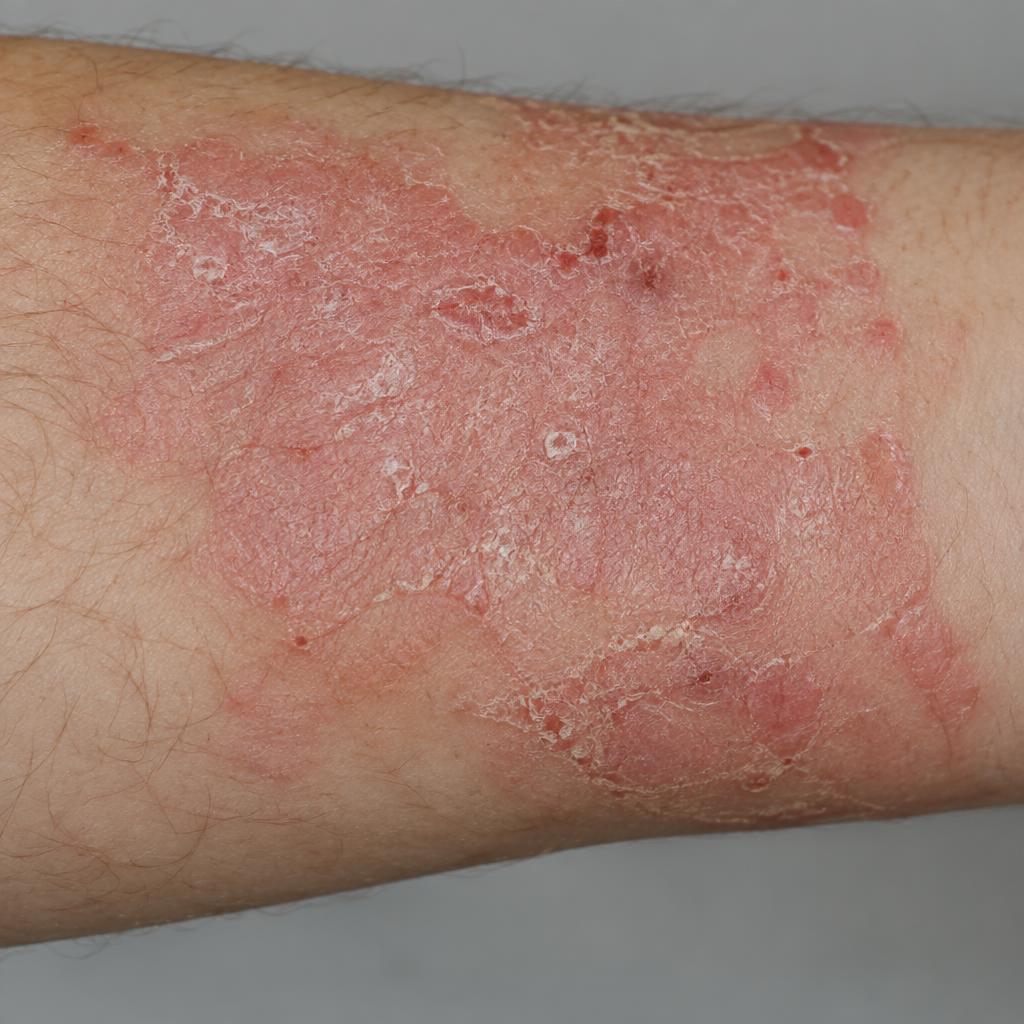
Macro framing acceptable; mild specular highlight on the superior margin.
Ill-defined erythematous scaly plaque with excoriation and reported pruritus on a flexural site.
Distribution is compatible; reported wool contact is a plausible irritant trigger.
Partially coin-shaped areas present but borders are not discrete.
Scale is fine rather than thick silvery; borders are not sharply demarcated.
No annular advancing edge with central clearing observed.
The photo of the arm shows a red, dry and flaky patch with scratch marks. This pattern is most consistent with an eczema-type inflammation. It is not a diagnosis - a clinician should confirm it.
SUPPORTIVE CARE
- Fragrance-free emollient applied several times daily
- Lukewarm, short showers; pat dry rather than rub
- Avoid wool and known irritants against the area
- Keep nails short to limit scratching damage
WHAT TO ASK YOUR DOCTOR
- Could this be eczema or a reaction to something I touch?
- Which moisturiser and strength of cream suits this area?
- How long should I use a steroid cream before reviewing?
- What signs mean I should come back sooner?
- Rapid spread, fever or spreading warmth would require same-day care
- Weeping, honey-coloured crust or pus suggests secondary infection
GENOMIC INTELLIGENCE NETWORK
Encodes filaggrin, which aggregates keratin filaments in the outer epidermis.
Barrier integrity and hydration; widely studied in atopic skin phenotypes.
Add genomic layer with RobGenes
Align this phenotype with the patient's own variant data.
LONGITUDINAL COMPARISON